Blood Test History: Heart Disease Risk
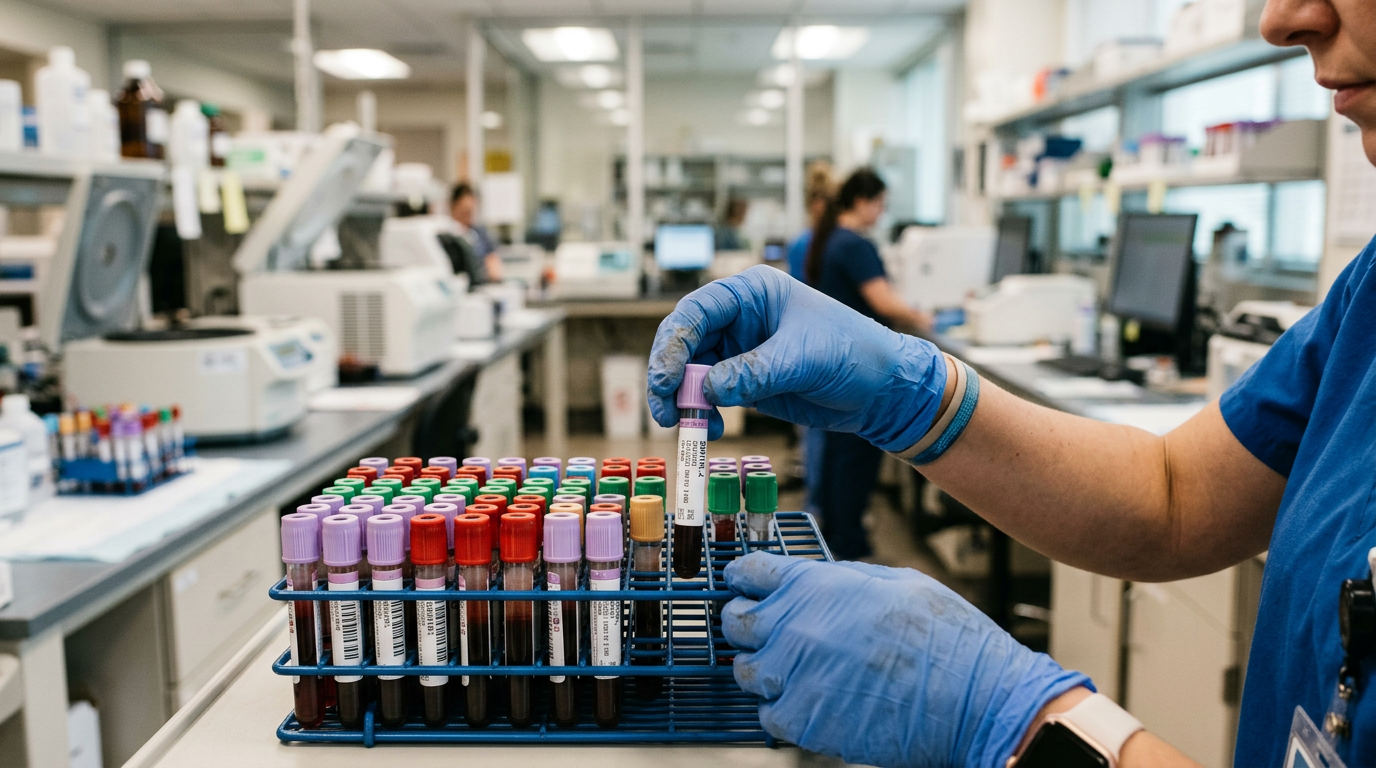
By Maria Shafiq | Founder & Health Research Writer, The Veins Vercel | Updated: 29 September 2026
How Your Blood Test History Could Reveal Future Heart Disease Risk
Evaluating your longitudinal blood test heart disease risk provides a critical window into vascular health. Most people treat routine lab results as isolated snapshots in time.
However, arterial disease develops quietly across decades rather than overnight. Single laboratory screenings often miss subtle, progressive biological decline.
In contrast, analyzing your cumulative blood test history uncovers occult endothelial damage early. Trajectory trends reveal whether circulating lipids, chronic inflammation, and metabolic stress actively stiffen your arterial tree.
By tracking biomarkers over consecutive years, clinicians can accurately calculate your real-world blood test heart disease risk. Consequently, tracking these vital metrics allows you to intervene before irreversible plaque calcification occurs.
+-----------------------------------------------------------------------------------+
|                        ISOLATED SNAPSHOT VS. TRAJECTORY TREND                     |
+-----------------------------------------------------------------------------------+
  Isolated Single Test (Year 5)  --> Normal LDL-C (98 mg/dL) | Clinical Assumption: Safe
                                      (Misses 5-year systemic vascular exposure)
                                      vs.
  Longitudinal History (Years 1-5)
  Year 1: hs-CRP: 0.6 mg/L | Fasting Glucose: 84 mg/dL  | Triglycerides: 85 mg/dL
  Year 3: hs-CRP: 1.4 mg/L | Fasting Glucose: 94 mg/dL  | Triglycerides: 130 mg/dL
  Year 5: hs-CRP: 2.8 mg/L | Fasting Glucose: 104 mg/dL | Triglycerides: 175 mg/dL
                                      |
  Clinical Insight: Progressive microvascular inflammation & cumulative plaque risk
+-----------------------------------------------------------------------------------+
What Blood Tests Reveal About Heart Health
Blood does not function as a static fluid. Instead, circulating blood carries cellular debris, inflammatory cytokines, and metabolic fuel throughout your vascular network.
The interior luminal surface of every blood vessel contains a delicate endothelial cell layer. When biochemical toxins circulate continuously, they injure this delicate lining.
First, inflammatory enzymes strip away the protective endothelial glycocalyx shield. Exploring endothelial glycocalyx integrity and circulation explains how this barrier loss triggers arterial vulnerability.
Second, damaged endothelial cells express sticky adhesion molecules that capture passing lipoproteins. In response, atherogenic particles penetrate the subendothelial space and oxidize.
Tissue macrophages then consume these oxidized lipids, transforming into inflammatory foam cells that initiate atherosclerotic plaque. Standard physical exams cannot detect this microscopic cellular degradation.
However, routine venous blood draws capture the exact molecular markers of this vascular cascade Source: National Institutes of Health. Tracking these laboratory markers across time exposes active endothelial injury long before arterial lumens narrow.
7 Key Biomarkers to Track for Vascular Longevity
Evaluating your long-term cardiovascular risk requires tracking seven fundamental serum biomarkers. Each marker reflects a unique mechanical or inflammatory failure point within the circulatory system.
+-----------------------------------------------------------------------------------+
|                        THE VASCULAR BIOMARKER SPECTRUM                            |
+-----------------------------------------------------------------------------------+
  [Atherogenic Lipids]    --> LDL-C, HDL-C, Triglycerides, & Lipoprotein(a)
              |
  [Inflammatory Drivers]  --> High-Sensitivity C-Reactive Protein (hs-CRP)
              |
  [Endothelial Toxins]    --> Plasma Homocysteine (Degrades Elastin & NO)
              |
  [Glycemic Stressors]    --> Fasting Blood Glucose & Glycated Hemoglobin (HbA1c)
              |
  Combined Evaluation: Pinpoints subclinical endothelial decay & arterial stiffening
+-----------------------------------------------------------------------------------+
1. LDL and HDL Cholesterol Fractions
Low-density lipoprotein cholesterol (LDL-C) measures the cholesterol carried by low-density particles. While cells require cholesterol for membrane repair, excess ApoB-containing LDL particles penetrate injured vascular walls.
High-density lipoprotein cholesterol (HDL-C) transports excess tissue cholesterol back to the liver for excretion. However, modern vascular research confirms that HDL quality matters more than raw quantity.
When systemic inflammation spikes, HDL particles lose their protective antioxidant capacity. Maintaining an optimal total cholesterol-to-HDL ratio below 3.5:1 protects arterial elasticity Source: American Heart Association.
2. Serum Triglycerides
Triglycerides represent circulating packages of stored fatty acids. Elevated levels (above 150 mg/dL) signal impaired lipid clearance and delayed liver metabolism.
Furthermore, high triglycerides indicate the presence of dense, highly atherogenic remnant lipoproteins. These remnant particles slip easily through permeable endothelial cell junctions.
Combining high triglycerides with low HDL-C confirms the atherogenic lipid triad. This pattern accelerates coronary plaque formation significantly.
3. High-Sensitivity C-Reactive Protein (hs-CRP)
The liver synthesizes C-reactive protein in direct response to interleukin-6 (IL-6) inflammatory signaling. While standard CRP tests detect acute infections, high-sensitivity CRP (hs-CRP) quantifies low-grade vascular inflammation:
-
Low Vascular Risk: Values below 1.0 mg/L.
-
Moderate Vascular Risk: Values between 1.0 and 3.0 mg/L.
-
High Vascular Risk: Values exceeding 3.0 mg/L.
Sustained elevations in hs-CRP prove that arterial linings endure continuous inflammatory friction Source: PubMed Central.
4. Plasma Homocysteine
Homocysteine represents an intermediate amino acid generated during normal methionine metabolism. When genetic mutations or B-vitamin deficiencies halt recycling pathways, homocysteine accumulates in circulation.
Excess homocysteine directly injures vascular endothelial cells. Specifically, it uncouples endothelial nitric oxide synthase (eNOS) and degrades structural elastin fibers.
Consequently, arteries lose compliance and stiffen rapidly. Reviewing arterial stiffness vs venous insufficiency clarifies how elastin loss drives high-pressure arterial disease.
5. Fasting Blood Glucose
Fasting blood glucose measures the concentration of free sugar circulating in blood plasma after an eight-hour fast. Optimal vascular ranges sit strictly between 72 and 85 mg/dL.
When fasting glucose creeps above 100 mg/dL, patients enter the prediabetic range. High circulating sugar generates reactive oxygen species that deactivate vasodilating nitric oxide immediately.
6. Glycated Hemoglobin (HbA1c)
Glycated hemoglobin reflects your average blood sugar concentration over the preceding ninety days. When glucose lingers in circulation, it binds irreversibly to hemoglobin molecules inside red blood cells.
Elevated HbA1c (above 5.6%) accelerates the synthesis of toxic Advanced Glycation End-products (AGEs). These sticky sugar compounds cross-link vascular collagen bundles, making vessel walls rigid.
Furthermore, chronic glucotoxicity destroys microscopic capillary networks. Reviewing diabetic peripheral neuropathy triggers and mechanisms reveals how sustained glycation starves peripheral microvessels.
7. Lipoprotein(a) [Lp(a)]
Lipoprotein(a) consists of an LDL-like particle bound covalently to a specialized glycoprotein called apolipoprotein(a). Serum concentrations are roughly 80% to 90% genetically determined.
Because of its unique molecular shape, Lp(a) resembles plasminogen, a protein that dissolves blood clots. Consequently, elevated Lp(a) (above 50 mg/dL or 125 nmol/L) promotes clot formation while delivering oxidized phospholipids directly into arterial walls Source: PubMed. Every adult should measure Lp(a) at least once during their lifetime.
| Biomarker | Ideal Physiological Target | Primary Vascular Failure Mode | Clinical Testing Frequency |
| LDL-C | <70–100 mg/dL (ApoB <80 mg/dL) | Subendothelial lipid accumulation | Annually (Every 6 months if high) |
| Triglycerides | <100 mg/dL (Ratio TG:HDL <2:1) | Circulating remnant particle toxicity | Annually |
| hs-CRP | <0.8 mg/L | Endothelial inflammation and plaque rupture | Every 6 to 12 months |
| Homocysteine | <8.0–9.0 $\mu\text{mol/L}$ | Elastin degradation; eNOS uncoupling | Annually |
| Fasting Glucose | 72 to 85 mg/dL | Acute microvascular oxidative stress | Every 6 months |
| HbA1c | <5.4% | Collagen glycation; arterial stiffening | Every 6 months |
| Lipoprotein(a) | <30 mg/dL (<75 nmol/L) | Thrombogenesis and oxidized lipid delivery | Once in a lifetime baseline |
How Long-Term Biomarker Trends Predict True Risk
Single blood tests provide only static snapshots of your physiology. In contrast, the human vascular tree responds directly to the cumulative area under the curve.
+-----------------------------------------------------------------------------------+
|                        CUMULATIVE AREA UNDER THE CURVE                            |
+-----------------------------------------------------------------------------------+
  YEAR 1:  LDL-C: 110 mg/dL  --> Minimal subendothelial retention
  YEAR 5:  LDL-C: 125 mg/dL  --> Gradual fatty streak formation
  YEAR 10: LDL-C: 140 mg/dL  --> Active inflammatory macrophage infiltration
  YEAR 15: LDL-C: 155 mg/dL  --> Dense calcified fibroatheroma formation
                                 |
  Clinical Insight: Vascular damage reflects (Concentration) x (Exposure Time)
+-----------------------------------------------------------------------------------+
Cardiologists evaluate this cumulative burden using the concept of pack-years or cholesterol-years. Ingesting or circulating elevated lipids over a brief period causes minimal structural injury.
However, sustaining an LDL-C of 140 mg/dL across two decades infuses immense lipid mass into the arterial intima. Concurrently, evaluating your glycemic trajectory uncovers early metabolic resistance.
For example, a fasting glucose rising by 3 mg/dL annually signals impending beta-cell failure years before diabetes diagnosis. Furthermore, upward trends in both hs-CRP and triglycerides highlight accelerating vascular strain.
Tracking trends across your blood test history allows preventative cardiologists to calculate your personalized blood test heart disease risk. Combining laboratory trends with modern predictive platforms, such as those evaluated in AI heart disease prediction breakthroughs, achieves unparalleled diagnostic accuracy.
5 Targeted Prevention Strategies to Improve Lab Markers
When blood test trends reveal rising cardiovascular risk, targeted lifestyle protocols can stabilize endothelial function and reverse metabolic decline:
+-----------------------------------------------------------------------------------+
|               5 PILLARS OF DAILY VASCULAR RESTORATION                             |
+-----------------------------------------------------------------------------------+
  1. Polyphenol & Nitrate Nutrition --> Boosts eNOS; lowers hs-CRP and blood pressure
  2. Targeted Micronutrient Timing  --> Resolves elevated homocysteine via methylation
  3. Continuous Zone 2 Aerobic Work --> Burns triglycerides; enhances insulin sensitivity
  4. Circadian Sleep Architecture   --> Lowers nocturnal cortisol and fasting glucose
  5. Structured Intermittent Fasting--> Triggers cellular autophagy and clears AGEs
+-----------------------------------------------------------------------------------+
1. Optimize Diet with Dietary Nitrates and Polyphenols
Consuming whole foods rich in inorganic nitrates stimulates endothelial nitric oxide production via the enterosalivary axis. Vegetables like wild arugula, red beets, and Swiss chard provide abundant nitrates.
Exploring nitric oxide foods for venous compliance explains how dietary nitrates dilate vessels and lower systemic blood pressure.
Concurrently, consume polyphenol-dense whole foods. Reviewing our guide on the apple biohacking tool for longevity illustrates how quercetin reduces systemic inflammation and blunts LDL oxidation.
2. Support Methylation to Lower Homocysteine
Clearing toxic homocysteine requires adequate methyl-donor micronutrients:
-
Bioactive B-Vitamins: Consume active methylfolate (L-5-MTHF), methylcobalamin (B12), and pyridoxal-5-phosphate (B6). These cofactors drive methionine synthase, converting homocysteine safely into methionine.
-
Trimethylglycine (Betaine): Found naturally in beets and spinach, betaine fuels alternative liver methylation pathways.
-
Mineral Timing: Understanding zinc timing and interactions ensures proper trace mineral absorption to support metabolic enzymes.
3. Deploy Regular Zone 2 Aerobic Conditioning
Engaging in 150 to 180 minutes of low-intensity Zone 2 cardio weekly dramatically improves metabolic markers. Rhythmic muscle contractions deplete intramuscular glycogen, prompting cells to express GLUT4 transporters.
Consequently, muscle tissue clears circulating glucose rapidly without requiring excess insulin. Furthermore, Zone 2 exercise accelerates mitochondrial fat oxidation, driving elevated serum triglycerides down naturally Source: American Heart Association Guidelines.
4. Protect Sleep Architecture and Autonomic Rest
Chronic sleep fragmentation elevates nocturnal cortisol and sympathetic nervous tone. This hormonal surge stimulates liver gluconeogenesis, elevating morning fasting glucose levels.
Understanding how REM sleep protects your heart details how restorative sleep lowers inflammatory hs-CRP and facilitates arterial repair.
5. Practice Circadian Time-Restricted Eating
Confining daily food consumption to an 8- to 10-hour window improves insulin sensitivity and stimulates cellular autophagy. Diurnal fasting periods allow cells to break down damaged proteins and clear advanced glycation products.
Reviewing time-restricted eating and vascular health shows how intermittent fasting lowers triglycerides, HbA1c, and resting blood pressure.
When to See a Doctor for Cardiovascular Evaluation
Lifestyle habits support daily vascular resilience effectively. However, certain lab abnormalities and physical symptoms require immediate professional clinical care.
+-----------------------------------------------------------------------------------+
|                        CARDIOVASCULAR WARNING FLAGS                               |
+-----------------------------------------------------------------------------------+
  ACUTE EMERGENCY RED FLAGS:
  - Sudden crushing chest tightness, squeezing, or heaviness
  - Pain radiating to the jaw, neck, back, or left arm
  - Unexplained shortness of breath with cold sweats or nausea
                                         |
  CRITICAL ACTION: Call emergency services (911) immediately. Do not drive.
+-----------------------------------------------------------------------------------+
High-Risk Lab Thresholds Requiring Physician Oversight
Schedule a prompt evaluation with a board-certified cardiologist or preventative physician if your records reveal:
-
Fasting LDL-C exceeding 190 mg/dL (suggests familial hypercholesterolemia).
-
Serum Lipoprotein(a) exceeding 50 mg/dL or 125 nmol/L.
-
Persistent hs-CRP exceeding 3.0 mg/L without an identifiable infection.
-
Fasting plasma homocysteine exceeding 15 $\mu\text{mol/L}$.
-
HbA1c climbing above 6.5% on repeat testing.
A specialist can order advanced anatomical imaging, including a Coronary Artery Calcium (CAC) scan or a Coronary Computed Tomography Angiography (CCTA). These non-invasive scans quantify physical plaque volume within coronary arteries directly.
Frequently Asked Questions About Blood Tests and Heart Disease
Can a blood test predict future heart disease risk accurately?
Yes. Longitudinal blood tests reveal cumulative biological exposure to atherogenic particles, inflammatory cytokines, and glucotoxicity. Tracking trends over several years provides vastly superior risk prediction compared to an isolated test.
Why is fasting insulin more informative than fasting glucose?
Fasting glucose remains normal for years because the pancreas compensates by pumping out excess insulin. Measuring fasting insulin uncovers insulin resistance decades before glucose levels climb into diabetic ranges.
What is the difference between LDL cholesterol and ApoB?
LDL-C measures the total weight of cholesterol inside low-density particles. In contrast, Apolipoprotein B (ApoB) counts the exact number of atherogenic particles in circulation. Because each atherogenic particle carries one ApoB molecule, measuring ApoB provides a more accurate assessment of plaque risk.
Does high hs-CRP always indicate heart disease?
No. C-reactive protein is a non-specific acute-phase reactant. Bacterial infections, acute physical trauma, or autoimmune flares can cause transient spikes. However, a persistent hs-CRP reading between 1.0 and 3.0 mg/L in the absence of infection confirms chronic vascular inflammation.
How often should adults undergo comprehensive cardiovascular blood testing?
Healthy young adults should check a comprehensive lipid panel, fasting glucose, and hs-CRP every two to three years. Adults over age forty, or those with a strong family history of premature heart disease, should test annually.
Conclusion
Your personal blood test history is not a collection of disposable numbers. Rather, it represents an ongoing medical ledger detailing the biological resilience of your vascular tree.
Evaluating your cumulative blood test heart disease risk empowers you to look beyond static snapshots. By tracking longitudinal trajectories in ApoB, triglycerides, hs-CRP, and HbA1c, you can identify microscopic endothelial distress decades before clinical events occur.
Managing cardiovascular risk requires consistent, data-driven action. Pair routine biomarker tracking with whole-food anti-inflammatory nutrition, daily Zone 2 walking, and restorative sleep habits.
Take ownership of your laboratory history today to safeguard your arteries and ensure lifelong cardiovascular vitality.
Editorial Note
This article was independently researched and written based on current publicly available peer-reviewed nutritional literature and does not represent the views of, and is not affiliated with, any external publication referenced.
References
-
National Institutes of Health (NIH). The Role of Biomarkers in Cardiovascular Disease Risk Prediction. PubMed Central. https://pubmed.ncbi.nlm.nih.gov/31951408/
-
Grundy, S. M., et al. (2019). 2018 AHA/ACC/AACVPR/AAPA/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Blood Cholesterol: A Report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines. Circulation, 139(25), e1082–e1143. https://doi.org/10.1161/CIR.0000000000000625
-
Ridker, P. M. (2018). High-sensitivity C-reactive protein and cardiovascular risk: from concept to clinical practice. PubMed Central, 40(4), 481–488. https://pubmed.ncbi.nlm.nih.gov/30343216/
-
Kronenberg, F., et al. (2022). Lipoprotein(a) in atherosclerosis and cardiovascular disease: consensus statement from the European Atherosclerosis Society. PubMed, 43(39), 3925–3946. https://pubmed.ncbi.nlm.nih.gov/35926752/
-
Arnett, D. K., et al. (2019). 2019 ACC/AHA Guideline on the Primary Prevention of Cardiovascular Disease: A Report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines. Circulation, 140(11), e596–e646. https://doi.org/10.1161/CIR.0000000000000678
-
Humphrey, L. L., et al. (2008). Homocysteine level and coronary heart disease incidence: a systematic review and meta-analysis. Mayo Clinic Proceedings, 83(11), 1203–1214. https://doi.org/10.4065/83.11.1203
-
Sniderman, A. D., et al. (2019). Apolipoprotein B Particles and Cardiovascular Risk: A Comprehensive Meta-Analysis. JAMA Cardiology, 4(12), 1287–1295. https://doi.org/10.1001/jamacardio.2019.3780
Editorial Note: This article was independently researched and written based on current publicly available health information and does not represent the views of, and is not affiliated with, any external publication referenced.